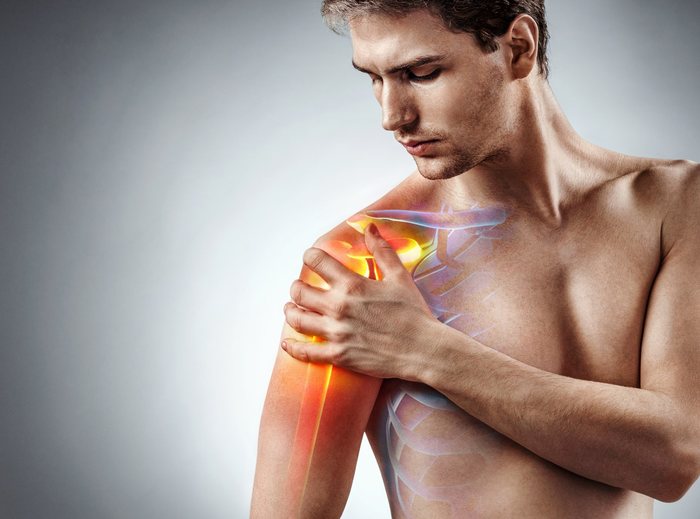
What is shoulder tendinopathy?
Shoulder tendon anatomy
The shoulder is stabilised by a set of four tendons, those of the rotator cuff (supraspinatus, infraspinatus, teres minor, subscapularis), plus the long head of biceps tendon.[1] These tendons pass through a narrow space under the acromion and both move and stabilise the joint with every arm movement. Shoulder tendinopathy refers to painful damage to one or more of these tendons, without a tear necessarily being present.
Why do these tendons become painful?
Pain appears when the shoulder tendons are repeatedly loaded beyond their capacity to adapt, particularly during overhead movements. An imbalance between the shoulder blade’s stabilising muscles, too rapid an increase in training volume, or poor sporting technique are the most common causes of tendon overload.

Symptoms and diagnosis of shoulder tendinopathy
Typical pain and its triggers
The pain is usually felt on the front or side of the shoulder, triggered by overhead movements, throwing or cocking the arm, and sometimes simply by carrying a load with a straight arm. It can also show up at night, particularly when sleeping on the affected side, and often comes with a feeling of fatigue or weakness during repeated effort.
Differential diagnosis
Several types of shoulder pain can look like shoulder tendinopathy:
- Shoulder impingement, often behind the tendon overload before it sets in
- Supraspinatus tendinopathy, a more specific form of rotator cuff tendinopathy
- Rotator cuff deficit, worth considering if there’s a clear or persistent loss of strength
- Frozen shoulder, where the loss of mobility is global rather than just painful within a specific arc
Causes and risk factors
Shoulder tendinopathy most often develops from a gradual build-up of strain, rarely from a single traumatic event.
Biomechanical and personal factors
- An imbalance between the shoulder blade’s stabilising muscles and the rotator cuff muscles
- A too-rapid increase in training volume or intensity
- Poor sporting technique that increases the strain with every repetition
- Stiffness in the posterior capsule or a rounded-shoulder posture
Which sports contribute to shoulder tendinopathy?
Any sport that repeatedly or intensively places demand on the shoulder overhead carries a particular risk:
- Swimming, especially front crawl and butterfly
- Tennis and racquet sports
- Volleyball and handball (smashing, serving)
- Throwing sports (javelin, baseball)
- Weight training with heavy overhead presses
- Climbing and overhead-gripping sports
Treating shoulder tendinopathy in rehab with a sports physio
The goal of treatment is to progressively strengthen the cuff tendons and the shoulder blade’s stabilising muscles, while temporarily reducing the load on the shoulder until the pain settles.
- 1Reducing pain and managing load
- 2Shoulder and shoulder-blade mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Eccentric strengthening
- 6Rotator cuff work
- 7Correcting sporting technique
- 8Strengthening under sport-specific load
- 9Progressive return to your sport
- 10Return to competition
“It’s not that the tendon is fragile, it’s that the load needs to be better dosed and distributed.”
Strengthening, the cornerstone of treatment
Strengthening the rotator cuff and the shoulder blade’s stabilising muscles (trapezius, serratus anterior) helps better distribute the strain on the shoulder tendons. This is completed by correcting sporting technique, since inefficient shoulder mechanics increase the strain with every repetition.
In brief
- Strengthening the rotator cuff
- Strengthening the shoulder-blade stabilisers
- Progressive correction of sporting technique
- Gradual return: mobility, then load, then sport
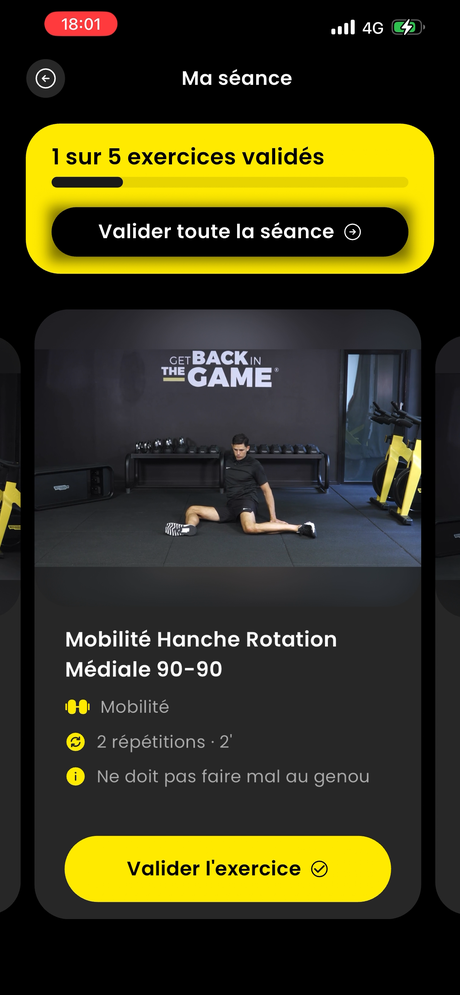
Ready to take your shoulder tendinopathy seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not necessary and isn’t the most effective solution. It’s better to temporarily adapt your activity by reducing the movements that clearly reproduce the pain, while staying physically active and starting cuff strengthening as soon as possible.
Think you might have a different shoulder injury?
Take your free test in 3 minutes flat.
When should you see a specialist for shoulder tendinopathy?
If the pain persists for more than three to four weeks despite adapting your activities, or if it comes with a clear loss of strength or systematically wakes you at night, a medical opinion is recommended to rule out a tendon tear.
Expected recovery timeline for shoulder tendinopathy
Shoulder tendinopathy progresses well in the vast majority of cases with well-run rehab. Clear improvement is usually seen within a few weeks, with a full return to sport following several weeks of progressive strengthening of the rotator cuff and shoulder blade stabilisers.
Preventing recurrence
Once the pain has resolved, a few measures help limit the risk of it coming back:
- Keep up rotator cuff and shoulder blade stabiliser strengthening long-term
- Progress the volume of overhead movements cautiously after a break or a new season
- Pay attention to sporting technique, especially in throwing or racquet sports
- Don’t ignore discomfort that reappears, a sign that the imbalance is creeping back
The HOPP care programmes to treat your shoulder tendinopathy and get back to sport
For lasting recovery, shoulder tendinopathy requires a progressive rebalancing of forces around the joint. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
A programme that adapts to you every day
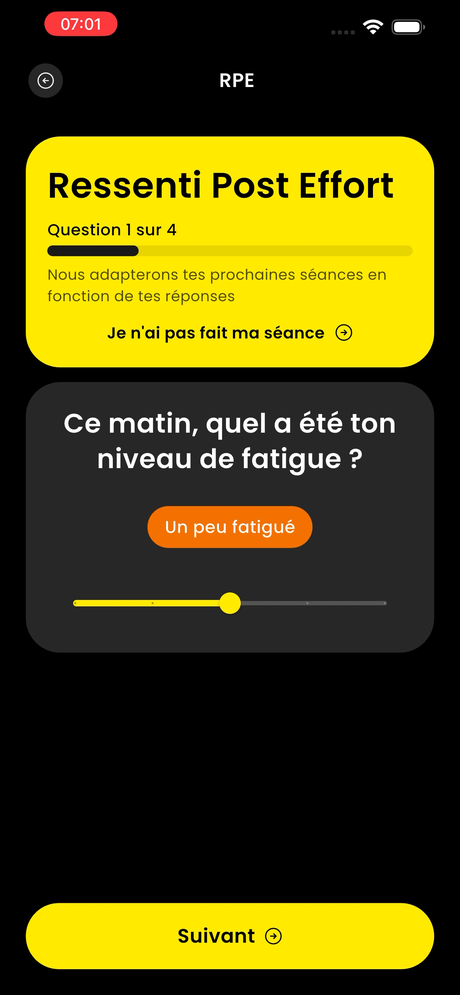
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your shoulder is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Can I keep playing sport with shoulder tendinopathy?
In most cases, yes, by temporarily adapting your volume and avoiding the overhead movements that reproduce the pain, while starting cuff strengthening in parallel.
How long does it take to recover from shoulder tendinopathy?
A structured programme generally brings clear improvement within a few weeks, with a full return to sport after several weeks of progressive strengthening.
Are tendinopathy and tendinitis the same thing?
The term “tendinopathy” is now preferred because it covers the various possible mechanisms (overload, degeneration, inflammation), whereas “tendinitis” implies inflammation that isn’t always present.[2]
What’s the difference between shoulder tendinopathy and shoulder impingement?
Shoulder impingement is a mechanical catching of the tendons under the acromion, often the root cause of tendinopathy if it isn’t corrected in time. Shoulder tendinopathy refers to damage to the tendon itself once the overload has set in. Both are treated with the same progressive strengthening approach.
How can you stop shoulder tendinopathy from coming back?
Keeping up regular rotator cuff and shoulder blade stabiliser strengthening, progressing training volume cautiously, and good movement technique are the best ways to limit recurrence once the pain has resolved.
Scientific references
- La Rose J, Madrazo-Ibarra A, Varacallo M. Anatomy, Rotator Cuff. StatPearls, NCBI Bookshelf, National Library of Medicine (NIH). ncbi.nlm.nih.gov/books/NBK441844
- Khan KM, Cook JL, Kannus P, Maffulli N, Bonar SF. Time to abandon the “tendinitis” myth. BMJ, 2002;324(7338):626-627. PubMed : pubmed.ncbi.nlm.nih.gov/11895810
- Park HB, Yokota A, Gill HS, El Rassi G, McFarland EG. Diagnostic accuracy of clinical tests for the different degrees of subacromial impingement syndrome. Journal of Bone and Joint Surgery (American), 2005;87(7):1446-1455. PubMed : pubmed.ncbi.nlm.nih.gov/15995110
This page is based on peer-reviewed scientific publications. It remains a general self-assessment tool and does not replace medical advice.