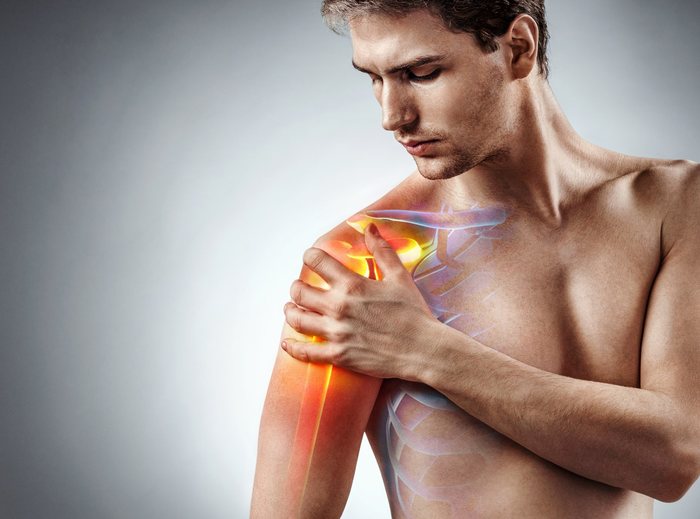
What is a rotator cuff deficit?
Rotator cuff anatomy
The rotator cuff is made up of four muscles (supraspinatus, infraspinatus, teres minor, subscapularis) whose tendons wrap around the head of the humerus and provide both mobility and stability to the shoulder.[1] A cuff deficit is a loss of strength or function in all or part of these muscles, ranging from simple functional weakness to an actual tendon tear.
Why does this deficit appear?
This deficit can result from progressive wear linked to age and repeated strain, an advanced untreated tendinopathy, or acute trauma causing a partial or complete tear of one or more tendons. In athletes, it’s most often progressive wear favoured by overhead sports practised intensively over many years.[5]

Symptoms and diagnosis of a rotator cuff deficit
Typical signs of the deficit
The deficit shows up as a loss of strength when raising or rotating the arm, sometimes with trembling during a resistance test, quick arm fatigue with effort, and occasionally night pain if there’s an inflammatory component too.
Differential diagnosis
Several shoulder conditions can present a similar loss of strength:
- A cuff tendinopathy without a tear, where the weakness is mainly due to pain inhibition
- Shoulder impingement, a possible cause of the deficit if it progresses without treatment
- A neurological issue (suprascapular nerve), rarer, worth considering if the deficit is isolated and marked with no associated pain
Causes and risk factors
A cuff deficit most often results from progressive wear or the progression of an untreated tendinopathy.
Biomechanical and personal factors
- Progressive wear linked to age and repeated strain
- An advanced, untreated tendinopathy
- Acute trauma causing a partial or complete tear
- Intensive, long-term practice of overhead sports
Which sports are affected by this deficit?
This deficit mainly affects athletes practising intensively and over time sports that load the shoulder overhead:[5]
- High-level swimming
- Tennis and badminton practised intensively
- Volleyball and handball
- Weightlifting and weight training
- Throwing sports
- Jobs and sports with repetitive arm movements
Treating a rotator cuff deficit in rehab with a sports physio
The goal of treatment is to strengthen the cuff’s remaining tendons and muscles to compensate for the deficit, while also working on the shoulder’s overall mechanics to optimise available function.
- 1Reducing pain and managing load
- 2Shoulder and shoulder-blade mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Eccentric strengthening
- 6Rotator cuff work
- 7Correcting sporting technique
- 8Strengthening under sport-specific load
- 9Progressive return to your sport
- 10Return to competition
DEMONSTRATION
Video by Hemrick, co-founder of HOPP.
“A deficient tendon is compensated for by the muscles that remain, not by inactivity.”
Compensatory strengthening, the cornerstone of treatment
Targeted strengthening of the cuff’s remaining muscles and the deltoid effectively compensates for the deficit in an affected tendon. Working on shoulder blade mechanics also optimises the shoulder’s overall function, often with satisfactory functional results even with a partial tear.
In brief
- Targeted strengthening of the cuff’s remaining muscles
- Compensatory deltoid strengthening
- Optimising shoulder blade mechanics
- Gradual return: mobility, then load, then sport
Ready to take your rotator cuff deficit seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not the best option for an established deficit: progressive, well-dosed strengthening of the remaining structures is what restores satisfactory shoulder function.
Think you might have a different shoulder injury?
Take your free test in 3 minutes flat.
When should you see a specialist for a rotator cuff deficit?
A medical opinion is recommended to confirm the extent of the deficit with a clinical examination and suitable imaging, particularly in the case of a sudden loss of strength following trauma, to discuss whether surgical repair might be worthwhile given your age and activity level.
Expected recovery from a rotator cuff deficit
The outlook mainly depends on the extent of the deficit and the compensatory strengthening put in place. A clear functional improvement is generally seen after several weeks of rehab, even though an existing tendon tear won’t repair itself spontaneously.
Slowing the deficit’s progression
Certain measures help preserve shoulder function and limit the deficit from worsening:
- Keep up regular strengthening of the cuff’s remaining muscles and the deltoid
- Adapt your volume of repeated overhead movements
- Don’t ignore a painful tendinopathy that could progress into a more significant deficit
- See a doctor if you experience a sudden loss of strength, which can signal an acute tear
The HOPP care programmes to treat your cuff deficit and get back to sport
This deficit requires targeted, progressive strengthening to optimise your shoulder’s function. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
A programme that adapts to you every day
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your shoulder is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Do I need surgery for this deficit?
Not systematically. Many athletes regain satisfactory function through rehab alone, with surgery mainly considered if conservative treatment fails or the deficit is very significant in a young, active athlete.
Can I keep playing sport with this deficit?
In many cases, yes, by adapting your activity and following a compensatory strengthening programme suited to your level of deficit.
Will this deficit get worse over time?
It depends on its cause. Well-conducted strengthening often stabilises shoulder function over time, even with a partial tendon tear.
How can I tell if my deficit comes from a tendinopathy or a tear?
Only imaging (ultrasound or MRI) can confirm a tendon tear.[4] Clinically, a tendinopathy without a tear is often accompanied by pain that inhibits strength, while a tear causes more pronounced weakness, sometimes with trembling on the resistance test.[3]
How long before I can get back to sport?
A progressive return is often possible after several weeks of compensatory strengthening, first reintroducing movements without overhead load, then gradually increasing intensity.