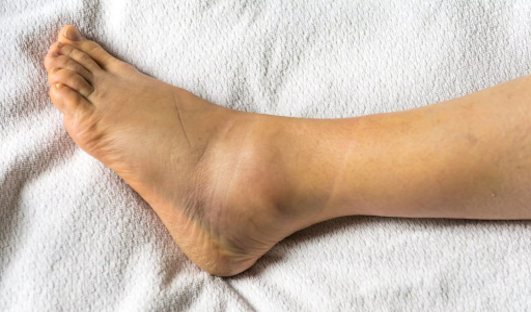
What is peroneal tendinopathy?
Peroneal tendon anatomy
The peroneal muscles (longus and brevis) run along the outer side of the leg and their tendons pass behind the outer ankle bone before reaching the foot. They play a key role in lateral ankle stability, particularly in preventing sprains. This tendinopathy frequently affects athletes with a history of ankle sprains.
Why do these tendons become painful?
Pain appears when the peroneal tendons are repeatedly loaded beyond their capacity, often linked to residual ankle instability following one or more previous sprains. An ankle that regularly “gives way” constantly stresses these stabilising tendons, which eventually weakens them.

Symptoms and diagnosis of peroneal tendinopathy
Typical pain and its triggers
The pain sits along the back-outer edge of the ankle, just behind the outer ankle bone, sometimes with mild, localised swelling along the tendon path. It’s typically triggered by running on uneven ground, changes of direction, lateral loading, and resisted eversion of the foot (turning the sole outward against resistance). It often flares up after returning to activity following a recent or old sprain.
Differential diagnosis
Several types of outer-ankle pain can resemble this tendinopathy, which is why a precise assessment matters:
- A recent ankle sprain, with sharper ligament pain, often with diffuse swelling and bruising
- Peroneal tendon subluxation, which shows up as a clear snapping or shifting sensation of the tendon behind the ankle bone during certain movements
- An ankle joint condition, more linked to stiffness and diffuse joint pain
Causes and risk factors
This tendinopathy develops almost always in connection with residual ankle instability, rather than starting from an initially fragile tendon.[1]
Risk factors
- A history of one or more insufficiently rehabbed ankle sprains
- Residual ankle proprioceptive deficit, which keeps functional instability going[2]
- High-arched feet or a varus alignment, which increases lateral strain on the ankle
- Too rapid an increase in training volume or intensity
- Unsuitable footwear or a sole worn down on the outer edge
Which sports contribute to peroneal tendinopathy?
Any sport with unstable footing or fast changes of direction exposes these tendons:
- Basketball and handball
- Football on uneven ground
- Trail running and hiking
- Racquet sports
- Dance
- Mountain sports (skiing, climbing)
Treating peroneal tendinopathy in rehab with a sports physio
The goal of treatment is to strengthen the peroneal tendons while working on overall ankle stability, to address the often underlying cause of this tendinopathy.
- 1Reducing pain and managing load
- 2Ankle mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Eccentric strengthening
- 6Ankle proprioceptive work
- 7Correcting technique and footing
- 8Strengthening under sport-specific load
- 9Progressive return to running
- 10Return to competition
“A painful peroneal tendon often calls for more stability, not just less load.”
Strengthening and stability, the cornerstones of treatment
Strengthening the peroneal tendons is combined with comprehensive ankle proprioceptive work, essential for restoring active stability that durably protects these tendons against overload and sprain recurrence.
In brief
- Progressive strengthening of the peroneal tendons
- Ankle proprioceptive work
- Treating the underlying instability
- Gradual return: mobility, then load, then sport
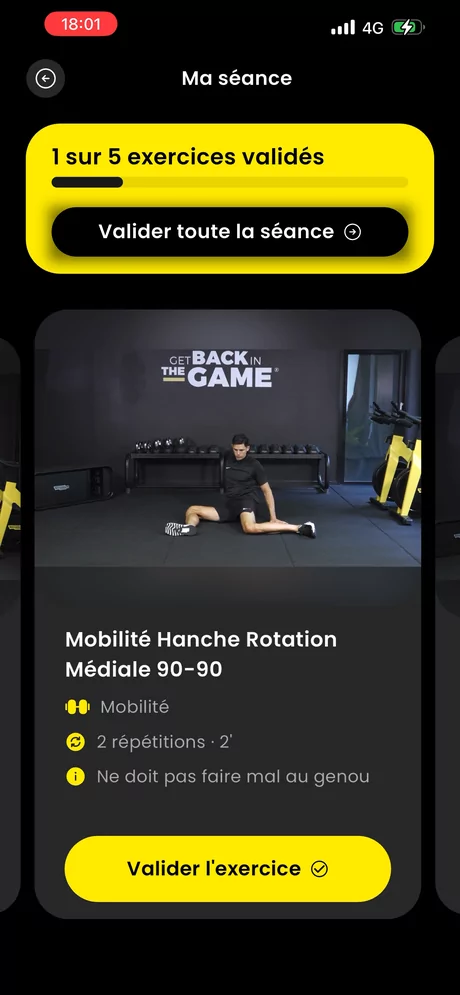
Exercises for peroneal tendinopathy
These exercises follow the main strengthening steps covered above, with concrete movements to work through progressively. Only increase the load if the pain stays mild and settles quickly after the exercise.
- 1Isometric eversion: press the outer edge of your foot against a wall or your hand, hold for 30 to 45 seconds, with no sharp pain.
- 2Eversion with a resistance band (concentric): band around the forefoot, push the foot outward against the resistance, 3 sets of 15 reps.
- 3Eccentric eversion: same movement, but focus on a slow, controlled return inward (3 to 4 seconds), a cornerstone of tendon strengthening.
- 4Single-leg balance: 30 to 45 seconds per side, eyes open then closed, to retrain ankle proprioception.
- 5Balance on an unstable surface: a wobble cushion or bosu ball, to progress toward more functional stability.
- 6Single-leg calf raises: on a step, 12 to 15 reps per leg, to reintroduce load through the calf and ankle.
- 7Controlled lateral jumps: at the end of the progression, to regain the reactivity needed for changes of direction in sport.
This progression follows the order of the rehab programme: always start with isometric work and mobility before introducing dynamic strengthening and unstable-footing exercises.
Ready to take your peroneal tendinopathy seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not necessary. It’s better to temporarily adapt the movements that clearly reproduce the pain, while starting strengthening and proprioceptive work as soon as possible.
Think you might have a different ankle injury?
Take your free test in 3 minutes flat.
When should you see a specialist for peroneal tendinopathy?
If the pain persists for more than four weeks, or if you feel a snapping sensation or clear tendon instability (which may suggest tendon subluxation), a medical opinion is recommended.
Expected recovery from peroneal tendinopathy
A structured programme generally brings clear improvement within a few weeks, with a full return to sport after several weeks of well-managed strengthening and proprioceptive work. The earlier ankle stability is retrained, the lower the risk of tendon recurrence, and of a new sprain.
Preventing recurrence
This tendinopathy readily comes back if stability work isn’t continued once the pain is gone.
- Keep up ankle proprioceptive work over the long term, even with no pain
- Regularly strengthen the peroneal tendons, particularly after any new sprain
- Adapt your footwear and stay careful on uneven ground
- Don’t ignore a residual feeling of ankle instability
- Progress carefully (the 10% weekly rule) when returning to activities with unstable footing or changes of direction
The HOPP care programmes to treat your peroneal tendinopathy and get back to sport
This tendinopathy requires a combined strengthening and stability approach. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
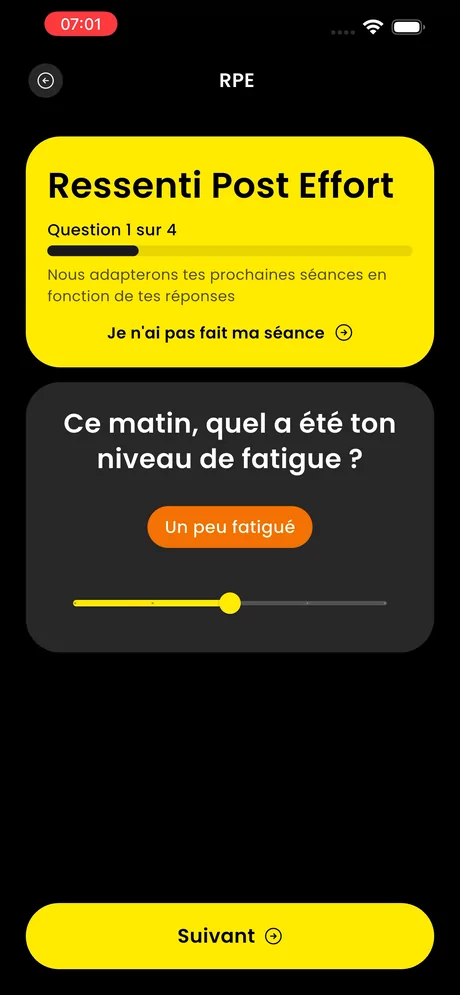
A programme that adapts to you every day
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your ankle is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Can I keep playing sport with this tendinopathy?
In most cases, yes, by temporarily adapting the movements that reproduce the pain, while starting strengthening and proprioceptive work in parallel.
How long does it take to recover?
A structured programme generally brings clear improvement within a few weeks, with a full return to sport after several weeks of progressive strengthening.
Why does my ankle stay unstable?
After one or more sprains, the ankle’s proprioceptive sensors can remain less effective if not specifically retrained, which explains the persistent feeling of instability.[2]
Can peroneal tendinopathy be hiding a poorly treated sprain?
Yes, this is actually the most common situation: an insufficiently rehabbed ankle sprain leaves residual instability that overloads the peroneal tendons over time.[1] Retraining ankle proprioception is then an integral part of treatment.
How do you tell peroneal tendinopathy apart from tendon subluxation?
Tendinopathy causes gradually worsening pain behind the outer ankle bone, with no clear instability. Subluxation shows up as a clear snapping or shifting sensation of the tendon during certain movements, which calls for a medical opinion to confirm the diagnosis.