


What is hip impingement?
Femoroacetabular impingement anatomy
Hip impingement, or femoroacetabular impingement, is an abnormal contact between the head of the femur and the rim of the socket that receives it (the acetabulum), during certain hip flexion and rotation movements. It’s linked to a particular bone shape (extra bone on the femoral neck or the acetabular rim), present in many athletes without necessarily causing symptoms.[1]
Why does this impingement become painful?
Pain appears when repeated hip flexion and rotation movements, particularly in a deep squat position or during extreme movements, cause repeated painful contact between the bony structures. Sports with a large hip range of motion (football, dance, martial arts) particularly expose athletes to this type of impingement.

The 3 types of femoroacetabular impingement
- Cam type: extra bone on the femoral neck, the most common in young athletes
- Pincer type: excess bony coverage on the acetabular rim
- Mixed type: a combination of both, the most common form in practice
Symptoms and diagnosis of hip impingement
Typical pain and its triggers
The pain is located in the groin crease, sometimes described with the “C sign” (the hand forms a C on the side of the hip to point to it). It’s classically triggered by prolonged sitting, deep flexion (a squat position), or sporting movements at an extreme hip range of motion.
How symptoms progress without treatment
Without treatment, stiffness and pain can progress, with the hip’s available range of motion gradually decreasing. A symptomatic impingement neglected for many years is also considered a risk factor for early hip osteoarthritis.[4]
Differential diagnosis
Several hip conditions can look like hip impingement :
- Adductor tendinopathy or psoas tendinopathy, with pain more linked to muscle contraction
- An isolated labral tear, without an associated bony impingement
- Early hip osteoarthritis, particularly in older athletes
Causes and risk factors
Hip impingement is primarily linked to a particular bone shape, but not every athlete with this shape develops symptoms.
Biomechanical and personal factors
- Bone shape (Cam, Pincer or mixed type)
- Intensive sporting activity before the end of growth, which can influence bone remodelling
- A lack of motor control of the pelvis and hip at extreme ranges of motion
- Associated stiffness in the posterior chain or adductors
Which sports contribute to symptomatic hip impingement?
All sports with a large range of hip flexion and rotation are particularly concerned:
- Football (kicking, changes of direction)
- Ice hockey
- Dance
- Martial arts
- Climbing
- Weight training with deep squats
Why do some athletes develop a symptomatic impingement and others don’t?
Bone shape alone doesn’t explain the pain : many athletes have an impingement visible on imaging without any symptoms. It’s often the combination of this bone shape with a high training volume at extreme hip ranges of motion that tips a silent impingement into a painful one.
Treating hip impingement in rehab with a sports physio
The goal of treatment is to optimise the hip’s available mobility and strengthen the stabilising muscles to limit the repeated strain causing the pain.
- 1Reducing pain and managing load
- 2Recovering available mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Hip proprioceptive work
- 6Closed-chain strengthening (weight-bearing)
- 7Optimising the sporting movement
- 8Strengthening under sport-specific load
- 9Progressive return to your sport
- 10Return to competition
“Hip impingement is managed by optimising the available mobility, not by trying to force the limited range of motion.”
Strengthening and available mobility, the cornerstones of treatment
The work focuses on optimising the hip’s genuinely available mobility, without forcing the range limited by the bony impingement, combined with strengthening the stabilisers to reduce repeated strain on the joint.
In brief
- Optimising available mobility
- Strengthening the stabilising muscles
- Correcting sporting technique if needed
- Gradual return: mobility, then load, then sport
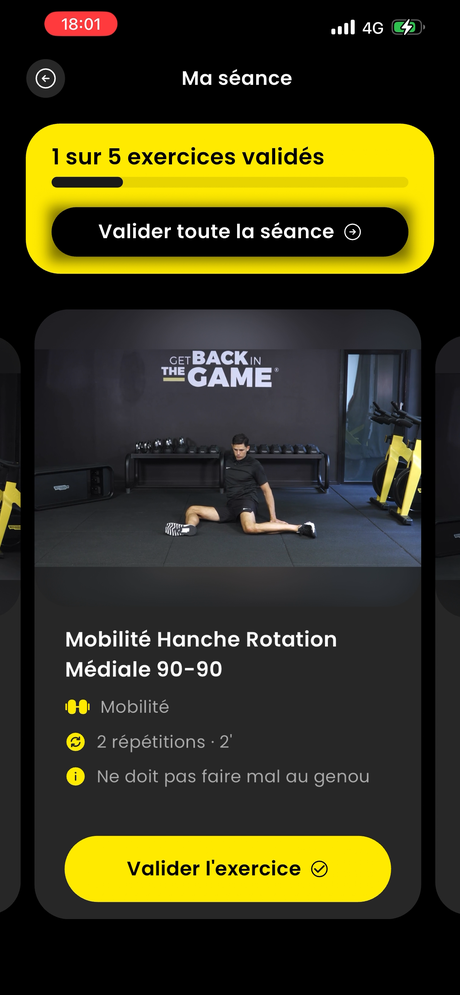
Ready to take your hip impingement seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not necessary. It’s better to temporarily adapt the deep flexion and rotation movements that clearly reproduce the pain, while starting rehab as soon as possible.
Think you might have a different hip injury?
Take your free test in 3 minutes flat.
When should you see a specialist for hip impingement?
If pain persists for more than four to six weeks despite rehab, or if mechanical locking is very marked, a medical opinion is recommended to precisely assess the bone shape and discuss further options.
What progress can you expect with a suitable programme?
The bone shape doesn’t change with rehab: what improves is the pain and function. Most athletes notice a clear improvement within 6 to 12 weeks of working on available mobility and strengthening, with better tolerance of everyday and sporting movements.[5]
Factors that influence this progress
- The type and extent of the bony impingement
- Consistency in mobility and strengthening work
- Adapting extreme ranges of motion in sport
- How long symptoms had been present before treatment started
Slowing the progression
A well-managed symptomatic impingement helps avoid worsening joint wear over the long term.
The 10% progression rule
Not increasing your training volume by more than 10% a week limits repeated strain on the impingement area.
Avoiding repeated extreme ranges of motion
Limiting repeated very deep hip flexion positions in training (beyond what your sport actually requires) reduces how often the bony structures make painful contact, without having to give up your sport.
The HOPP care programmes to treat your hip impingement and get back to sport
This impingement requires suitably managed mobility and load. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
A programme that adapts to you every day
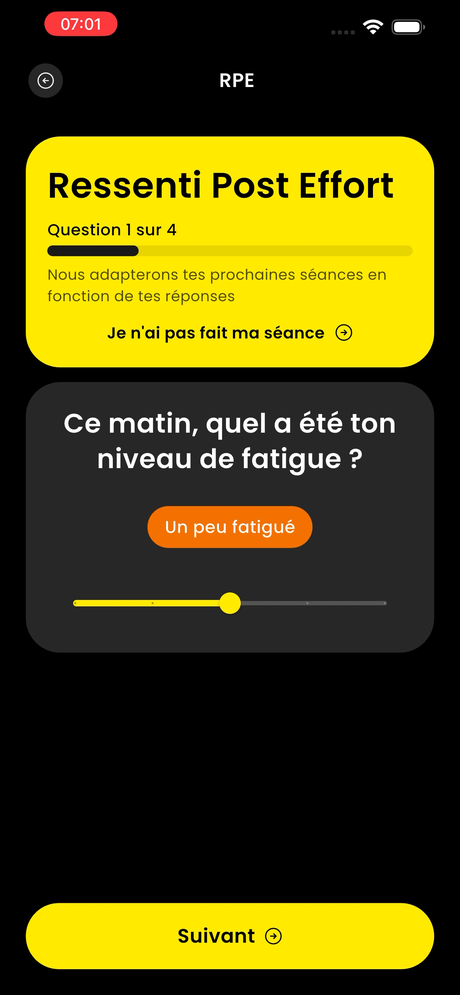
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your hip is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Will this impingement get worse over time?
Suitably managed load and well-conducted strengthening often durably stabilise symptoms, even though the bone shape itself doesn’t change.
Is surgery necessary?
Not systematically. Rehab often brings satisfactory functional improvement. Surgery is considered if well-conducted conservative treatment fails.
Can I keep playing sport with this impingement?
In many cases, yes, by temporarily adapting extreme hip movements and working on mobility and strengthening in parallel.
Does hip impingement always lead to osteoarthritis?
No, not systematically, but a symptomatic impingement neglected for several years increases the risk of premature cartilage wear.[4] Early treatment often helps limit this risk.
At what age does hip impingement appear?
Symptoms most often appear between ages 20 and 40 in athletes, although the bone shape behind the impingement usually forms during growth.



