


What is adductor tendinopathy (pubalgia)?
Adductor and pubic anatomy
The adductor muscles connect the pelvis (at the pubic bone) to the inner thigh and bring the leg back toward the body’s midline. Their tendons attach to the pubic bone, a convergence zone for many muscular and abdominal structures. Pubalgia, a term covering chronic groin pain, most often corresponds to adductor tendinopathy at its pubic attachment.
Why does this area become painful?
Pain appears when the adductors are repeatedly loaded beyond their capacity, particularly during changes of direction, ball strikes, or intense running efforts. A strength imbalance between adductors and abdominals, too rapid an increase in training volume, or poor recovery between sessions are common contributing factors.

Tendinitis or tendinopathy: what’s the difference?
We call it tendinitis when the tendon inflammation is recent and acute; we call it tendinopathy when the pain settles in over time, with microscopic tendon damage rather than simple inflammation. In the vast majority of chronic groin pain cases in athletes, it really is tendinopathy, even though the term “adductor tendinitis” is still widely used in everyday language to describe the same thing.
The 5 adductor muscles involved
The hip adductor group is made up of five muscles, all attaching on or near the pubic bone:
- Adductor longus, the most commonly affected, superficial and easily felt at the groin
- Adductor brevis, deeper
- Adductor magnus, the largest of the group
- Gracilis, the longest, running down to the knee
- Pectineus, the closest to the hip joint
Symptoms and diagnosis of adductor tendinopathy
Typical pain and its triggers
The pain is typically felt in the groin, sometimes radiating toward the inner thigh. It can affect one side only (right or left groin tendinitis) or both in cases of bilateral overuse. It’s most often triggered by striking a ball, sudden changes of direction, sprinting, or simply a resisted contraction of the adductors (squeezing the knees together). Some athletes describe discomfort that seems to appear for no apparent reason, without any impact: this is actually the sign of a gradual tendon overload, invisible as long as it stays below the tolerance threshold, until the pain kicks in.
How symptoms progress without treatment
Without proper care, the pain tends to appear earlier and earlier during effort, then to persist after training, and even at rest and at night in advanced cases. The main risk is chronic pain setting in, progressively limiting sports practice, with a tendon that tolerates load less and less well.
Differential diagnosis (hernia, pubalgia, stress fracture)
Several structures can cause similar groin pain, which is why a precise assessment matters:
- Inguinal hernia: a visible bulge at the groin, sometimes with a sensation of weakness in the abdominal wall
- Abdominal-origin pubalgia: pain triggered more by the abdominals (core bracing, sit-ups) than by the adductors
- Stress fracture of the femoral neck or pubis: deeper pain, often present even at rest, which requires imaging if in doubt
- Hip osteoarthritis: pain triggered more by hip rotation or flexion movements than by contracting the adductors
It’s the combination of these clinical elements (exact location, triggering movements, history) that helps point the diagnosis toward one origin or another.
Causes and risk factors
Adductor tendinopathy almost always results from an imbalance between the load placed on the tendon and its capacity to tolerate that load at a given moment.
Biomechanical and personal factors
- A strength imbalance between adductors and abdominals, very common in athletes who neglect core strengthening
- A lack of hip mobility, particularly in external rotation
- A strength asymmetry between the two legs
- A history of groin or hip injury
- Too rapid an increase in training volume or intensity
Which sports contribute to adductor tendinopathy?
Any sport with fast changes of direction and ball strikes carries a particular risk:
- Football/soccer, the most affected sport
- Ice hockey
- Rugby
- Racquet sports
- Athletics (sprinting, hurdles)
- Combat sports with changes of stance
Why groin pain with no apparent reason?
This is one of the most common situations: no impact, no fall, and yet pain sets in. It’s almost always explained by a gradual overload: an increase in training volume, more matches, or too quick a return after a break, which exceeds the tendon’s capacity to adapt without any single identifiable event. The tendon doesn’t “snap” all at once: it wears down progressively until the pain appears.
Treating adductor tendinopathy in rehab with a sports physio
The goal of treatment is to progressively strengthen the adductors and rebalance the strength ratio with the abdominals, while temporarily reducing load on the painful area.
Phase 1 – Pain reduction (isometric exercises)
In the first few days, the goal is to calm the pain without stopping everything: isometric contractions of the adductors (holding the contraction without moving, for example a ball squeezed between the knees) often give an immediate pain-relieving effect while keeping the tendon active.
Phase 2 – Progressive strengthening (eccentric)
Once the pain is better controlled, concentric then eccentric strengthening of the adductors becomes the priority: it’s this work, combined with core strengthening, that lets the tendon regain its capacity to handle load.
Phase 3 – Return to sport
The final phase progressively reintroduces the movements specific to the sport practised (strikes, changes of direction, sprints) before a full return to training and then to competition.
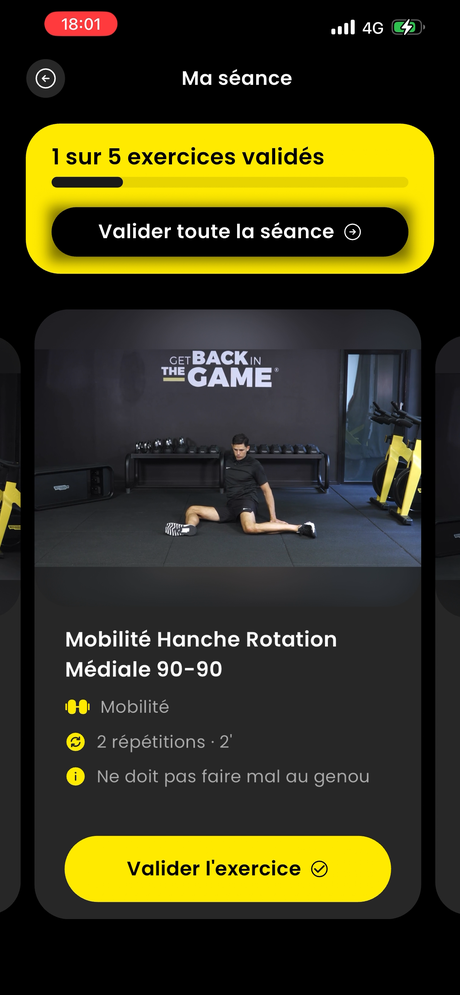
In practice, this programme breaks down into 10 concrete steps:
- 1Reducing pain and managing load
- 2Hip mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Eccentric strengthening
- 6Pelvic chain work
- 7Correcting sporting technique
- 8Strengthening under sport-specific load
- 9Progressive return to your sport
- 10Return to competition
DEMONSTRATION
Video by Hemrick, co-founder of HOPP.
“It’s not that the tendon is fragile, it’s that the load needs to be better dosed and distributed.”
Strengthening, the cornerstone of treatment
Progressive strengthening of the adductors, particularly eccentric work, combined with core abdominal work, rebalances the forces around the pubic bone and reduces repeated tension on this convergence zone.
In brief
- Progressive strengthening of the adductors
- Associated core abdominal work
- Eccentric strengthening
- Gradual return: mobility, then load, then sport
Ready to take your adductor tendinopathy (pubalgia) seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not necessary. It’s better to temporarily adapt the striking and change-of-direction movements that clearly reproduce the pain, while starting strengthening as soon as possible.
Think you might have a different hip injury?
Take your free test in 3 minutes flat.
When should you see a specialist for pubalgia?
If the pain persists for more than four to six weeks despite adapting your activities and following a well-run strengthening programme, a medical opinion is recommended to pinpoint the exact origin of the pain (tendon-related, abdominal or mixed).
Recovery time: how long does it take to recover from adductor tendinopathy?
There’s no single timeframe: pubalgia is one of the tendinopathies that demands the most patience. A clear day-to-day improvement in pain is often seen within 3 to 6 weeks of well-run rehab, but a full, confident return to full-intensity movements (striking, sprinting, changes of direction) more typically takes 6 to 12 weeks, sometimes several months for long-standing or neglected cases.
Factors that speed up or slow down recovery
- How long the pain had been present before treatment started (the earlier it’s addressed, the faster the recovery)
- How consistently you keep up strengthening, particularly eccentric work
- Following the load progression properly, without rushing back into full-intensity movements too soon
- Working the core abdominals alongside it, often underestimated
The most reliable marker isn’t the calendar but function: a successful return is judged by the absence of pain on sport-specific movements at full intensity, not just by the disappearance of discomfort at rest.
Preventing relapses
Pubalgia is an injury that often comes back if strengthening isn’t kept up once the pain has gone.
The 10% progression rule
To avoid overloading the tendon beyond what it can tolerate, a simple rule is to not increase training volume or intensity by more than 10% per week, whether that’s running distance, number of sprints, or strength-training load. It’s this gradual progression, more than rest, that protects the tendon in the long run.
The Copenhagen Adduction exercise
The Copenhagen Adduction is the reference exercise, validated by research, for preventing adductor tendinopathy in at-risk athletes (football and ice hockey in particular). In a side-lying position, the top foot resting on a bench and the bottom leg unsupported, the exercise involves holding then raising the hips, strongly engaging the adductors eccentrically. Done once or twice a week as prevention, it has shown a significant reduction in groin injury risk in several studies on footballers.
The HOPP care programmes to treat your pubalgia and get back to sport
This pubalgia requires comprehensive, progressive strengthening. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
A programme that adapts to you every day
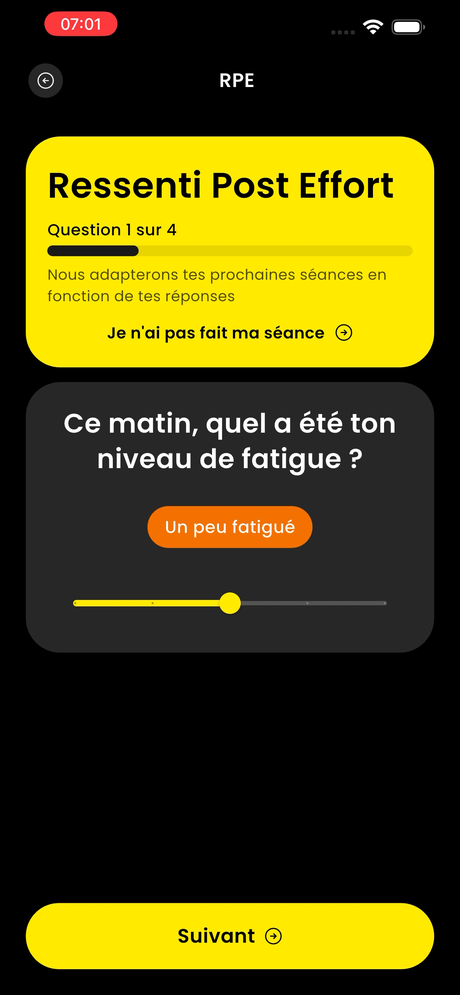
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your groin is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Can I keep playing sport with this pubalgia?
In most cases, yes, by temporarily adapting the movements that reproduce the pain, while starting strengthening in parallel.
How long does it take to recover?
Pubalgia can take longer to heal than other tendinopathies, with gradual improvement over several weeks to a few months depending on how long the symptoms have been present.
Why does pubalgia often come back?
Because it’s often linked to a broader strength imbalance (adductors/abdominals) that needs to be treated as a whole and maintained over time to prevent recurrence.
What causes adductor inflammation?
Most often a gradual tendon overload (increased training volume, more strikes or changes of direction) rather than an isolated impact, combined with a strength imbalance between the adductors and abdominals.
Groin tendinitis: how much rest do you need?
Total rest is generally neither necessary nor advisable: it’s better to temporarily adapt painful movements while starting strengthening, which protects and repairs the tendon more effectively than stopping completely.



