


What is golfer’s elbow (medial epicondylitis)?
Medial epicondyle anatomy
The medial epicondyle is the bony prominence on the inner side of the elbow, where the tendons of the wrist flexor and forearm pronator muscles attach. Medial epicondylitis, better known as “golfer’s elbow”, is a painful condition of these tendons at their attachment, the mirror image of tennis elbow but on the inner side.
Why does this area become painful?
Pain appears when the wrist flexor tendons are subjected to too much repeated load, typically during wrist flexion and forced pronation movements (a golf swing, throwing).[1] As with tennis elbow, it’s not limited to golfers and can affect any activity that heavily loads these tendons.

Golfer’s elbow vs tennis elbow: what’s the difference?
Both are elbow tendinopathies that respond to the same treatment principles, but affect opposite tendons: tennis elbow affects the wrist extensors on the outer side, golfer’s elbow affects the flexors on the inner side. Golfer’s elbow is notably less common than tennis elbow.[2]
The flexor muscles involved
Several tendons attach to the medial epicondyle:
- The flexor carpi radialis
- The flexor carpi ulnaris
- The pronator teres, which also contributes to forearm rotation
Symptoms and diagnosis of golfer’s elbow
Typical pain and its triggers
Pain sits on the inner side of the elbow, sometimes radiating into the forearm. It’s typically triggered by a golf swing (especially at impact), throwing, gripping in pronation, or a firm handshake.
How symptoms progress without treatment
Without treatment, pain tends to be triggered by increasingly minor movements, eventually interfering with simple activities like gripping an object or turning a key.
Differential diagnosis
Several types of elbow pain can resemble golfer’s elbow:
- Tennis elbow: the same condition, but on the outer side of the elbow
- Cubital tunnel syndrome (ulnar nerve compression): medial pain combined with tingling in the ring and little fingers, worth telling apart since treatment differs[3]
- Medial collateral ligament instability, more common in elite throwing athletes
Causes and risk factors
Golfer’s elbow results from repeated overload of the flexor tendons that exceeds their capacity to recover between bouts of strain.
Biomechanical and personal factors
- Incorrect swing technique, particularly excessive wrist rotation at impact
- Gripping a club or tool too tightly
- Lack of overall forearm strength
- A sudden increase in practice volume or manual activity
Which sports contribute to golfer’s elbow?
All sports and activities that heavily load wrist flexion and pronation carry a risk of this condition:
- Golf, at the moment of ball impact
- Throwing sports (baseball, javelin)
- Climbing and grip-intensive sports
- Weight training with heavy grip exercises
- Racquet sports
- Repetitive manual activities
Why does elbow pain appear with no obvious cause?
As with tennis elbow, golfer’s elbow affects many non-athletes too: it’s a cumulative overload injury, linked to repeated movements at work or at home. The tendon wears down gradually until it reaches the pain threshold, without any single identifiable event.
Treating golfer’s elbow in rehab with a sports physio
The goal of treatment is to progressively strengthen the wrist flexor tendons to restore their capacity to absorb load, while correcting the movement causing the overload.
Phase 1, reducing pain (isometric exercises)
In the first few days, isometric contractions of the wrist flexors often provide quick pain relief while keeping the tendon active.
Phase 2, progressive strengthening (eccentric)
Eccentric strengthening of the wrist flexors is the foundation of treatment: this is the work that lets the tendon regain its capacity to bear load.[4]
Phase 3, returning to sport or activity
The final phase progressively reintroduces specific movements (swing, gripping tools) before a full return to activity.
In practice, this programme breaks down into 10 concrete steps:
- 1Reducing pain and managing load
- 2Elbow and wrist mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Eccentric strengthening
- 6Overall forearm work
- 7Correcting sporting technique
- 8Strengthening under sport-specific load
- 9Progressive return to your sport
- 10Return to competition
“It’s not that the tendon is fragile, it’s that the load needs to be better dosed and distributed.”
Eccentric strengthening, the cornerstone of treatment
Strengthening the wrist flexors, particularly eccentrically, is the foundation of medial epicondylitis treatment.[4] It’s complemented by overall forearm work and, if needed, correcting technique (golf swing, work-related movement).
In brief
- Eccentric strengthening of the wrist flexors
- Progressive overall forearm strengthening
- Correcting technique if needed
- Gradual return: mobility, then load, then sport
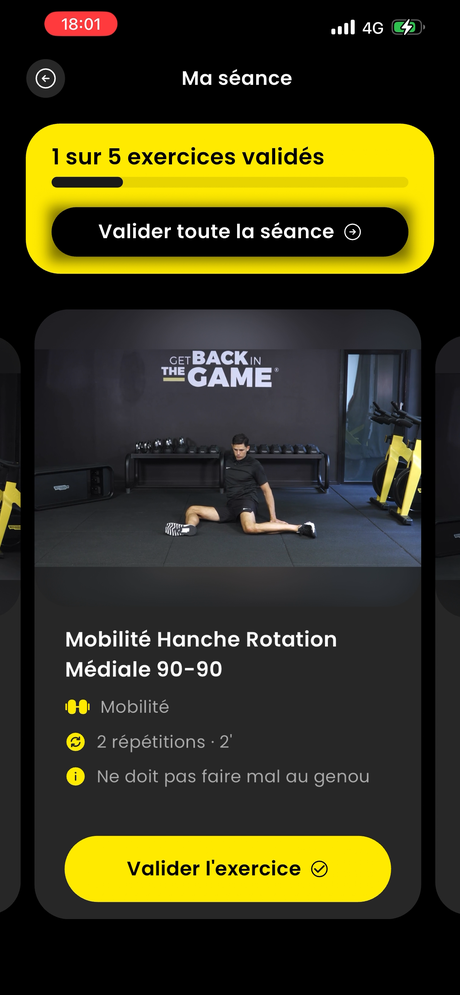
Ready to take your golfer’s elbow seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not the most effective solution. It’s better to temporarily adapt the movements that clearly reproduce the pain, while starting eccentric strengthening as soon as possible.
Think you might have a different elbow injury?
Take your free test in 3 minutes flat.
When should you see a specialist for golfer’s elbow?
If pain persists for more than four to six weeks despite adapting your activities and a well-conducted strengthening programme, a medical opinion is recommended to consider further treatments.
Recovery timeline: how long does it take to recover from golfer’s elbow?
Like tennis elbow, golfer’s elbow heals slowly. A clear improvement in day-to-day pain is often seen within 6 to 8 weeks of rehab, but a full return to full-intensity movements more typically takes 3 to 6 months.
Factors that speed up or slow down healing
- How long the pain had been present before treatment started
- Consistency of eccentric strengthening
- Correcting the technique or equipment involved
- Following a gradual load progression before returning to full-intensity movements
Preventing recurrence
Golfer’s elbow recurs easily if strengthening isn’t kept up and the movement responsible isn’t corrected.
The 10% progression rule
Not increasing your training or manual-activity volume by more than 10% per week durably protects the tendon from a new overload.
Ongoing eccentric strengthening
Regular eccentric wrist flexion work (light load or a resistance band, slow and controlled return), kept up even after rehab ends, helps maintain the tendon’s capacity to bear load. Good swing technique, reviewed with a professional if needed, rounds out this prevention.
The HOPP care programmes to treat your golfer’s elbow and get back to sport
This medial epicondylitis requires rigorous, progressive eccentric strengthening. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
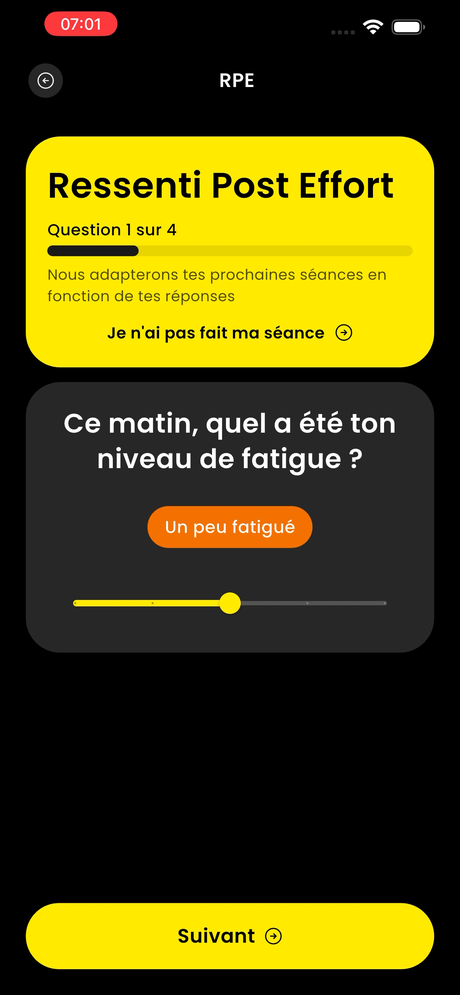
A programme that adapts to you every day
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your elbow is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Should I stop golf with this medial epicondylitis?
Not necessarily a complete stop, but a temporary adaptation of your volume and sometimes your swing technique, while starting eccentric strengthening in parallel.
How long does it take to recover from golfer’s elbow?
Medial epicondylitis can take longer to heal than other tendinopathies, with gradual improvement over several weeks to a few months depending on how long the symptoms have been present.
What’s the difference with tennis elbow?
Tennis elbow affects the wrist extensor tendons on the outer side of the elbow, while golfer’s elbow affects the flexor tendons on the inner side. Treatment principles are similar.
Can golfer’s elbow affect both arms?
In golfers, it’s often the lead arm (the left arm for a right-handed player) that takes the most strain at impact, but either arm can be affected depending on the movement and activity involved.
How can I adjust my swing to avoid a recurrence?
Excessive wrist break at impact is often to blame. Working with a golf professional, combined with flexor strengthening, can correct this movement and reduce the risk of recurrence.



