


What is hip osteoarthritis?
The anatomy of the hip joint
The hip is a joint bringing together the head of the femur and the pelvic socket, both covered in cartilage. Osteoarthritis is the gradual wear of this cartilage, leading to pain and stiffness. In athletes, it can appear earlier than in the general population, linked to repeated trauma or old, untreated hip impingement.
Why does this joint wear down?
Wear of the hip cartilage results from a combination of factors: repeated mechanical strain over many years of sporting practice, a history of trauma (fractures, dislocations), old hip impingement, or individual predisposition. In athletes, osteoarthritis isn’t inevitable and isn’t linked purely to age.

Coxarthrosis, the medical term for hip osteoarthritis
“Coxarthrosis” is the precise medical name for hip osteoarthritis (“coxa” meaning hip in Latin). Both terms describe the same thing: the gradual wear of the cartilage covering the head of the femur and the pelvic socket.
The structures involved
The hip joint involves several structures that can be affected by osteoarthritis:
- The head of the femur, covered in cartilage, which articulates within the pelvic socket
- The acetabulum, the socket in the pelvis that receives the femoral head
- The acetabular labrum, a ring of cartilage that stabilises the joint, often damaged in cases of old hip impingement
Symptoms and diagnosis of hip osteoarthritis
Typical pain and what triggers it
The pain is most often felt in the groin crease, sometimes radiating to the buttock, thigh or even down to the knee. It’s classically accompanied by morning stiffness that improves with movement (a “warm-up” effect), and triggered by prolonged walking, climbing stairs or sitting low for extended periods.
How symptoms progress without treatment
Without treatment, loss of mobility generally progresses before pain does, particularly in hip internal rotation. A limp can appear with prolonged effort, and pain-free walking distance tends to shrink over time.
Differential diagnosis
Several other causes of hip pain can resemble early-stage osteoarthritis:
- Hip impingement, often a precursor to osteoarthritis in young athletes, before established cartilage wear sets in[1]
- Adductor tendinopathy or psoas tendinopathy, which causes more anterior pain linked to muscle contraction
- Sciatica or referred low back pain, to be distinguished with a clinical examination
- Avascular necrosis of the femoral head, rarer, usually with a more sudden onset
Causes and risk factors
Hip osteoarthritis in athletes often results from a combination of individual predisposition and repeated mechanical strain on the joint.
Biomechanical and personal factors
- Old, untreated hip impingement
- Hip dysplasia (insufficient bony coverage of the femoral head)
- A history of trauma (fracture, dislocation)
- Excess weight, which increases strain on the joint
- Intensive sporting activity sustained over several years
Which sports are associated with hip osteoarthritis?
Any sport practised intensively over many years, or with a history of hip trauma, can be relevant here:
- Football and rugby over long careers
- Combat sports
- Intensive long-term running
- Sports with a history of hip trauma
- Professional dance
Why does this pain set in gradually?
Unlike an acute injury, osteoarthritis sets in slowly, with no single triggering event: it’s the build-up of mechanical strain on the cartilage, year after year, that eventually outpaces its capacity to regenerate. That’s why the pain often seems to appear “for no reason”, when in fact it’s the endpoint of a long-running process.
Treating hip osteoarthritis in rehab with a sports physio
The goal of treatment is to maintain optimal hip mobility and strengthen the surrounding muscles to better distribute strain and preserve function in the long run.
- 1Reducing pain and managing load
- 2Recovering available mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Hip proprioceptive work
- 6Closed-chain strengthening (weight-bearing)
- 7Optimising the sporting movement
- 8Strengthening under sport-specific load
- 9Progressive return to your sport
- 10Return to competition
DEMONSTRATION
Video by Hemrick, co-founder of HOPP.
“A joint that moves and gets stronger stays a joint that works, whatever its condition.”
Maintaining function, the cornerstone of treatment
Strengthening the hip’s stabilising muscles and maintaining regular active mobility helps preserve joint function and limit the progression of symptoms, even with established cartilage wear.
In brief
- Maintaining active mobility
- Strengthening the stabilising muscles
- Suitably managed sporting load
- Gradual return: mobility, then load, then sport
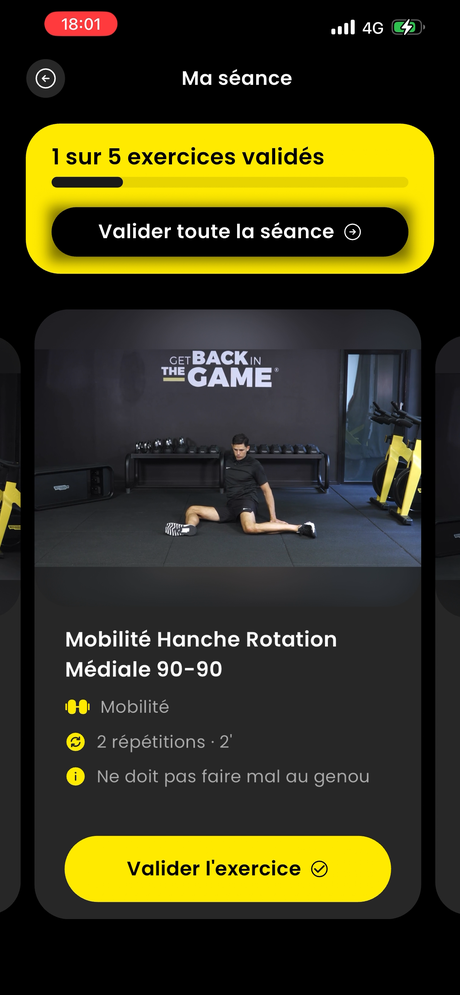
Ready to take your hip osteoarthritis seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Complete rest generally isn’t the best option for established osteoarthritis: maintaining suitable, regular activity is what best preserves hip function over time.
Think you might have a different hip injury?
Take your free test in 3 minutes flat.
When should you see a specialist for hip osteoarthritis?
A medical opinion is recommended to confirm the diagnosis with a clinical examination and suitable imaging, particularly in the case of pain that worsens despite rehab or a significant loss of mobility affecting everyday activities.
What progress can you expect with a suitable programme?
Cartilage doesn’t regenerate, so there’s no “cure” for osteoarthritis in the strict sense. What does improve favourably is pain and day-to-day function: most athletes who follow a strengthening and mobility programme notice a clear improvement within 6 to 12 weeks, with better tolerance for walking and activity.
Factors that influence this progress
- How worn the cartilage was when treatment began
- How consistently you keep up strengthening and mobility work
- Managing your weight
- Adapting the type and volume of sporting activity
Slowing the progression and protecting your hip
While osteoarthritis can’t be cured, its progression can be significantly slowed by simple, consistent habits.
Regular physical activity, your best ally
Contrary to popular belief, inactivity worsens osteoarthritis more than it protects against it: cartilage is nourished through movement.[2] Regular, moderate-impact activity (cycling, swimming, walking, strengthening) maintains mobility and strength around the joint, two factors that genuinely slow the progression of symptoms.
Managing your weight
Every extra kilo multiplies the strain the hip bears with each step.[3] Maintaining a suitable weight is one of the measures with the best-demonstrated effect on slowing the progression of hip osteoarthritis.
The HOPP care programmes to treat your hip osteoarthritis and get back to sport
This condition requires suitably managed load and regular strengthening. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
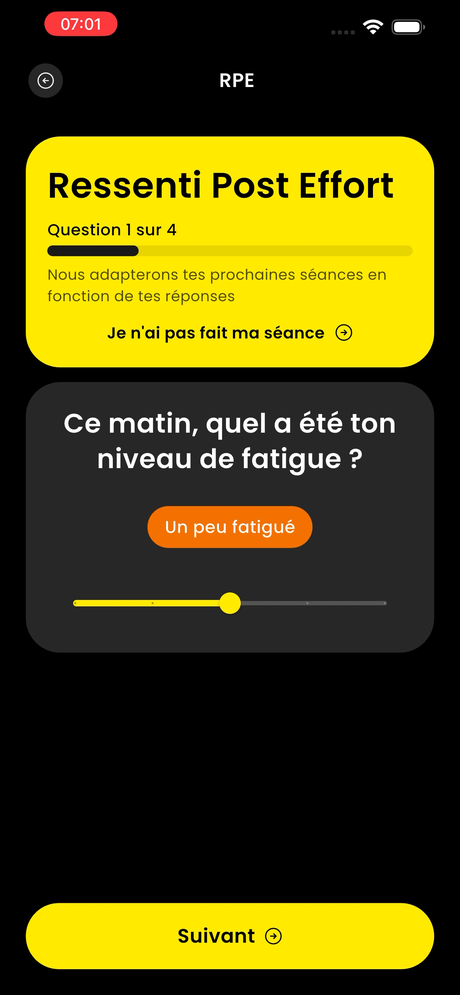
A programme that adapts to you every day
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your hip is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Do I need to stop sport with this osteoarthritis?
Not necessarily. Suitable, well-dosed activity is generally beneficial for maintaining hip function, rather than stopping completely.
Does sport make osteoarthritis worse?
Practised reasonably and under proper guidance, sport doesn’t worsen osteoarthritis. On the contrary, muscle strengthening and maintaining mobility are among the recommended treatments.
Is surgery necessary?
Rarely as a first option in athletes. Rehab and adapting your activity often manage symptoms satisfactorily for many years, with surgery (joint replacement) considered in the most advanced cases.
Does hip impingement always lead to osteoarthritis?
No, not systematically, but hip impingement left untreated for several years increases the risk of premature cartilage wear. Treating the impingement early often helps limit that risk.
Which sports are best with hip osteoarthritis?
Low-impact activities like swimming, cycling or walking are generally well tolerated and recommended. Running or sports with repeated jumping can often be continued in an adapted way, depending on individual tolerance.



