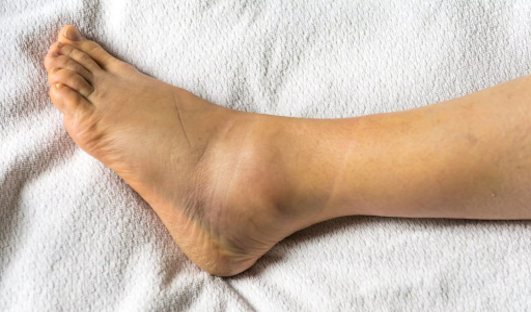
What is tibialis anterior tendinopathy?
Tibialis anterior anatomy
Tibialis anterior is the main muscle that lifts the foot, located on the outer side of the shin. Its tendon passes over the top of the ankle before attaching at the base of the first metatarsal and first cuneiform bone. It provides dorsiflexion of the foot and controls the heel strike with every step. It’s distinct from the other dorsiflexors (toe extensors) through its predominant role in controlling the ankle.
Why does this tendon become painful?
Pain appears when tibialis anterior is repeatedly overloaded eccentrically, particularly through controlling the heel strike at each stride, typically during downhill running or a sudden increase in training volume.[1] Lacing that’s too tight across the top of the foot can also irritate this tendon where it passes under the ankle’s retinacula.

Symptoms and diagnosis of tibialis anterior tendinopathy
Typical pain and its triggers
The pain is located on top of the ankle, along the tendon’s path to its insertion on the inner side of the foot. It’s triggered by actively pulling the foot up against resistance, by downhill running, or by lacing that’s too tight across the top of the foot. Unlike an acute muscle injury, the discomfort sets in gradually, often first appearing during warm-up before easing off, then becoming increasingly present during and after exertion.
Differential diagnosis
Several types of leg or ankle pain can look like this tendinopathy:
- Tibialis anterior muscle strain, an acute injury to the muscle belly in the leg rather than the tendon near the ankle
- Anterior tibial shin splints with suspected tibialis anterior tendinopathy, a more diffuse pain over the shin bone, sometimes combined with involvement of the same tendon
Causes and risk factors
This tendinopathy develops when the tibialis anterior tendon is repeatedly loaded eccentrically beyond its capacity to adapt.[2]
Biomechanical and personal factors
- A sudden increase in the volume or intensity of downhill running
- Lacing that’s too tight across the top of the foot, compressing the tendon under the retinacula
- An eccentric strength deficit in tibialis anterior
- A recent change of footwear or terrain
Which sports contribute to tibialis anterior tendinopathy?
Any sport with downhill running or repeated ground impact places strain on this tendon:
- Downhill running and trail running
- Hiking on hilly terrain
- Skiing (rigid boots)
- Football and sports with repeated sprints
- Sports with tight-fitting footwear across the top of the foot
Treating tibialis anterior tendinopathy in rehab with a sports physio
The goal of treatment is to progressively strengthen tibialis anterior to restore its capacity to control the heel strike, particularly through eccentric work.
- 1Reducing pain and managing load
- 2Ankle mobility
- 3Isometric strengthening
- 4Progressive concentric strengthening
- 5Eccentric strengthening
- 6Ankle proprioceptive work
- 7Correcting technique and footing
- 8Strengthening under sport-specific load
- 9Progressive return to running
- 10Return to competition
“It’s not that the tendon is fragile, it’s that the load needs to be better dosed and distributed.”
Eccentric strengthening, the cornerstone of treatment
Strengthening tibialis anterior, particularly through eccentric work to replicate its heel-strike-control role, restores its capacity to withstand the load specific to running, especially downhill.
In brief
- Progressive strengthening of tibialis anterior
- Specific eccentric work
- Adjusting footwear if needed
- Gradual return: mobility, then load, then sport
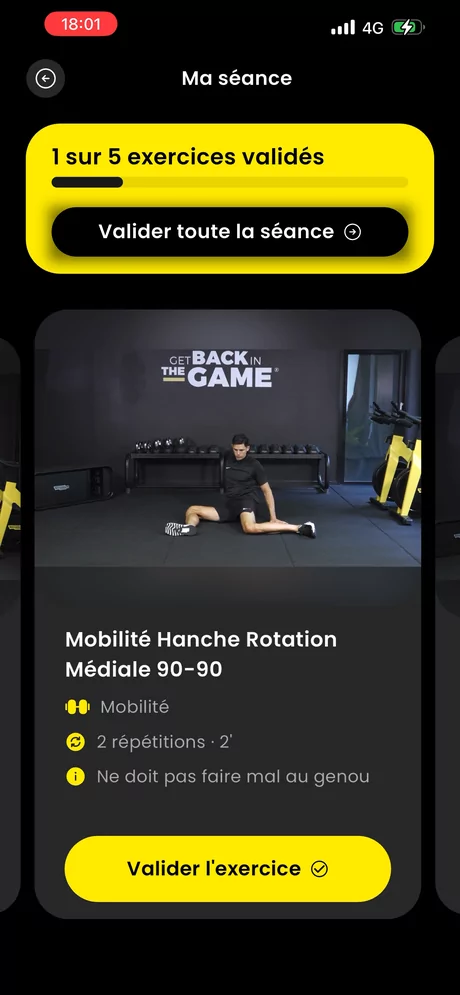
Ready to take your tibialis anterior tendinopathy seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest is generally not necessary. It’s better to temporarily adapt the volume of downhill running that clearly reproduces the pain, while starting strengthening as soon as possible.
Think you might have a different ankle injury?
Take your free test in 3 minutes flat.
When should you see a specialist for this tendinopathy?
If the pain persists for more than three to four weeks despite adapting your activities, or if you feel clear weakness lifting your foot, a medical opinion is recommended.
Expected recovery timeline for tibialis anterior tendinopathy
With appropriate treatment combining load management and eccentric strengthening, clear improvement is generally seen within a few weeks. As a chronic overload tendinopathy, the pain generally takes longer to resolve than an acute muscle injury: a full return to downhill running happens gradually, at the pace the tendon can tolerate.
Preventing recurrence
Once the pain has settled, a few measures help stop this tendinopathy from coming back:
- Keep up regular eccentric strengthening of tibialis anterior, even after recovery
- Gradually increase downhill running volume when resuming training or starting a new season
- Adjust your shoe lacing to avoid excessive compression across the top of the foot
- Stay alert to any sudden change of terrain or footwear
The HOPP care programmes to treat your tibialis anterior tendinopathy and get back to sport
This tendinopathy requires progressive eccentric strengthening. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
A programme that adapts to you every day
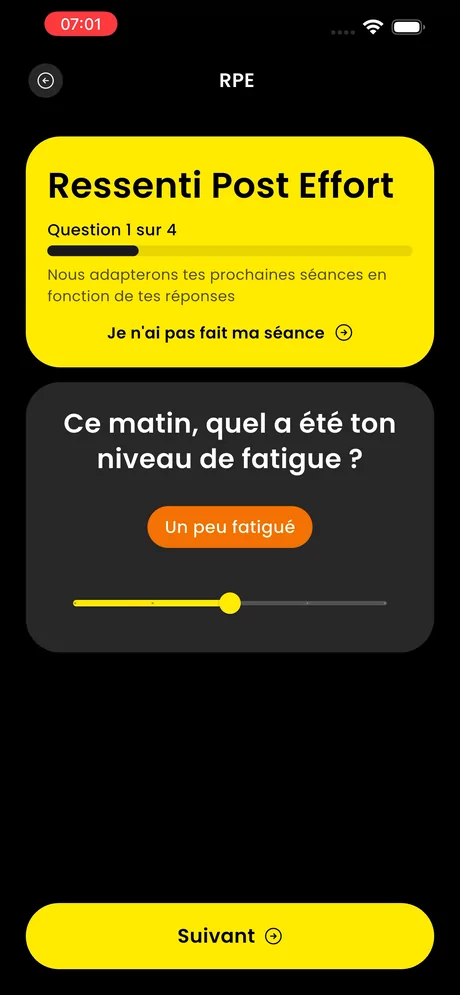
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your ankle is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.
Can I keep running with this tendinopathy?
In most cases, yes, by temporarily avoiding the downhill running that reproduces the pain, while starting strengthening in parallel.
How long does it take to recover?
A structured programme generally brings clear improvement within a few weeks, with a full return to sport after several weeks of progressive strengthening.
What’s the difference with foot dorsiflexor tendinopathy?
Tibialis anterior is the main dorsiflexor muscle and the one most often involved; the term “dorsiflexors” more broadly covers all the muscles that lift the foot and toes, of which tibialis anterior is one.
What’s the difference between this tendinopathy and shin splints?
Shin splints affect the membrane covering the shin bone, with diffuse pain over several centimetres, whereas tibialis anterior tendinopathy is localised to the tendon, on top of the ankle through to the inner foot. The two can coexist.
Should you change your shoes or lacing?
Lacing that’s too tight across the top of the foot can irritate the tendon where it passes under the ankle ligaments: loosening that area is often enough. A full shoe change is only needed if there’s noticeable wear or persistent discomfort.