What is quadriceps tendinopathy?
Quadriceps tendon anatomy
The quadriceps tendon connects the quadriceps muscle to the top of the kneecap. It’s what transmits force from the quadriceps to the kneecap and then to the patellar tendon, and absorbs much of the impact on every jump landing. It’s affected less often than the patellar tendon, but follows a similar pattern.
Why does this tendon become painful?
As with other tendinopathies, it’s an imbalance between the repeated strain placed on the tendon and its capacity to recover between loads. Movements that demand rapid force absorption in knee extension (jumps, landings, deep squats) particularly stress this tendon, especially with a rapid increase in training volume.

The stages of quadriceps tendon pain
Blazina classification (adapted)[1]
- Stage 1, pain only after activity
- Stage 2, pain at the start of activity, which fades with warm-up then returns afterwards
- Stage 3, pain during and after activity, which interferes with sport
- Stage 4, tendon rupture (rare, in cases of prolonged neglect)
Symptoms and diagnosis of quadriceps tendinopathy
Typical pain and its triggers
The pain sits just above the kneecap, at the quadriceps tendon attachment. It’s classically triggered by jumping, deep squats, going down stairs, or landing after a jump. It often progresses through the 4 Blazina stages described above.
How symptoms progress without treatment
Without proper care, the pain generally progresses from stage 1 (after activity only) toward more disruptive stages, eventually interfering with sport itself. The most serious risk, although rare, is tendon rupture from prolonged neglect of an already badly worn tendon.
Differential diagnosis
Several types of pain at the front of the knee can resemble quadriceps tendinopathy:
- Patellar tendinopathy, affecting the tendon below the kneecap
- Patellar syndrome, a more diffuse pain around the kneecap
- Suprapatellar bursitis, with more noticeable swelling above the kneecap
Causes and risk factors
Quadriceps tendinopathy results from an imbalance between the load placed on the tendon and its capacity to tolerate it.
Biomechanical and personal factors
- Older age, a period of lower tendon tolerance
- Intensive practice of strength sports (heavy squats, weightlifting)
- A deficit in eccentric quadriceps strengthening
- Too rapid an increase in training volume or load
Which sports contribute to quadriceps tendinopathy?
Sports that demand powerful or repeated knee extension carry a particular risk:
- Weightlifting and weight training with heavy squats
- Volleyball and basketball (repeated jumping)
- Athletics (jumping, sprinting)
- Football (striking, changes of footing)
- Sports with repeated jump landings
Why does knee pain appear for no apparent reason?
As with most tendinopathies, the pain most often results from gradual overload rather than an identifiable shock: an increase in squat or jump volume, with no single event to point to, gradually wears down the tendon until it crosses the pain threshold.
Treating quadriceps tendinopathy in rehab with a sports physio
The goal of treatment is twofold: quickly ease the pain, then restore the tendon’s capacity to withstand the demands of your sport, without lasting effects.
Phase 1 – Pain reduction (isometric)
In the first few days, isometric work for the quadriceps often has a quick pain-relieving effect, while keeping the tendon active.
Phase 2 – Progressive strengthening (eccentric)
Eccentric strengthening of the quadriceps is the foundation of treatment: this is the work that restores the tendon’s capacity to handle load.
Phase 3 – Return to sport
The final phase progressively reintroduces jumping and squats at full load before a complete return to training and then competition.
In practice, this programme breaks down into 10 concrete steps:
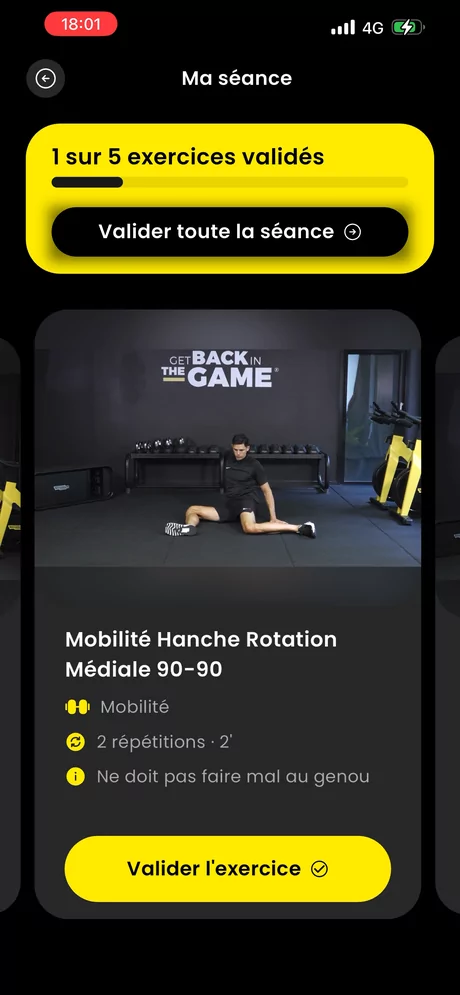
- 1Knee and hip mobility
- 2Pain-relieving isometric work
- 3Eccentric strengthening
- 4Progressive full-chain strengthening
- 5Proprioception
- 6Light plyometrics
- 7Reintroducing jumping
- 8Quantifying training load
- 9Return to running / your sport
- 10Return to competition
“It’s not that the tendon is fragile, it’s that the load exceeded its capacity to adapt at a given moment.”
Strengthening, the cornerstone of treatment
Isometric strengthening (contracting the quadriceps without movement) is often used first-line because it has a fast, well-documented pain-relieving effect.[2] It’s then complemented by eccentric work, or heavy, slow resistance loading, which stimulates tendon restructuring over several weeks.
In brief
- Isometric work first to calm the pain
- Eccentric / heavy, slow resistance to strengthen the tendon
- Progressive strengthening of the hip – knee – ankle chain
- Gradual return: mobility, then plyometrics, then jumping
Ready to take your quadriceps tendinopathy seriously?
Start the HOPP programme designed by sports physios.
Should you rest or keep playing sport?
Total rest isn’t the solution. While it can reduce pain in the short term, it also deprives the tendon of the mechanical stimulation it needs to remodel. During the acute phase, it’s better to adapt your activity: limit jumping and deep squats, while staying physically active and starting strengthening as soon as possible.
Think you might have a different knee injury?
Take your free test in 3 minutes flat.
When should you see a specialist for quadriceps tendinopathy?
If the pain persists for more than two to three weeks despite adapting your activities, or in the case of sudden, intense pain suggestive of a rupture, a medical opinion is recommended without delay. Ultrasound is the most useful exam for assessing the tendon.
Recovery time: how long does it take to recover from quadriceps tendinopathy?
Most athletes see clear improvement within 6 to 10 weeks of well-run rehab, with a full return to jumping and squatting at full load typically between 10 and 14 weeks. Long-standing cases (stage 3) often need more patience.
Factors that speed up or slow down recovery
- The Blazina stage at the time treatment starts
- How consistently you keep up eccentric strengthening
- Following the load progression properly before returning to jumping
- Managing your overall squat training volume
Preventing relapses
Quadriceps tendinopathy comes back easily if strengthening isn’t kept up once the pain has gone.
The 10% progression rule
Not increasing your squat or jump volume or load by more than 10% per week gives the tendon lasting protection against a new overload.
Ongoing eccentric strengthening
Regular slow eccentric squat work, kept up even after rehab has finished, helps maintain the tendon’s load capacity, particularly before the start of a season for sports with repeated jumping.
The HOPP care programmes to treat your quadriceps tendinopathy and get back to sport
Quadriceps tendinopathy requires a complete, progressive programme of care to heal durably. HOPP offers you a precise exercise programme, allowing you to get back to your activities as quickly as possible. By combining stretching, mobility, isometric and eccentric strengthening, and training management, HOPP supports you all the way back to the field.
The programme runs from 3 to 9 weeks depending on the injury and ends with a reconditioning phase allowing a return to competition in the best possible conditions. Each programme is designed by the HOPP team, made up of two sports physiotherapists who are experts in assessing and treating athletes. You’ll also find theoretical content throughout your progression, so you master every aspect of your recovery and can adjust your treatment independently. If needed, our team of physiotherapists is on hand to support you.
Essential
FROM INJURY TO
BACK TO YOUR ACTIVITIES
59€
One-time payment
“AT YOUR OWN PACE WITH
DAILY ADAPTATION”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
Performance
TO GET BACK TO SPORT
IN THE BEST CONDITIONS
79€
One-time payment
“GET BACK TO YOUR LEVEL
WITHOUT RISK OF RELAPSE”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility
- Strengthening
- Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
Expert
PERSONALISED VIDEO-CALL
SUPPORT, ANY TIME
149€
One-time payment
“A PHYSIO
WHENEVER YOU NEED”
- 100% of the treatment programme
- Daily personalisation
- Flexibility / Mobility, Strengthening, Proprioception
- Progress tracking
- Return-to-running programme
- Theoretical content included
- + 4-week return-to-play plan with 6 difficulty levels
- + 2 video calls with an expert sports physio / return check-up
A programme that adapts to you every day
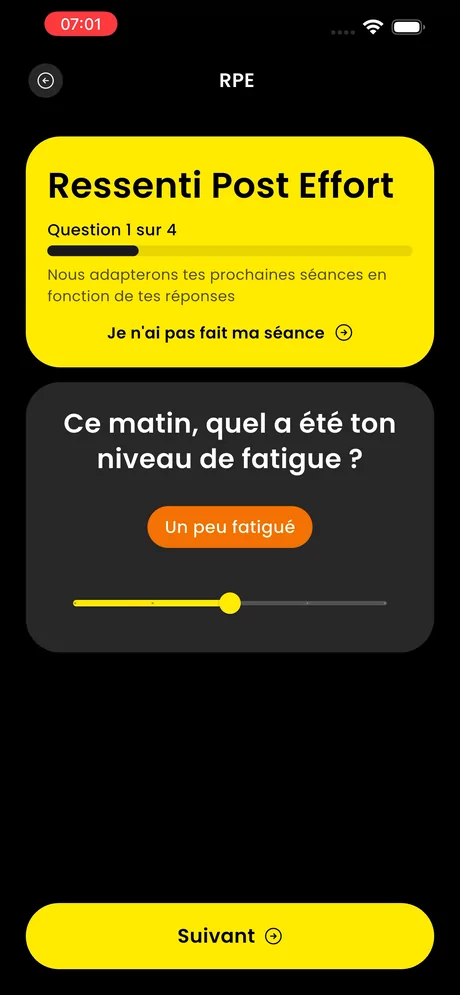
Every day, how you feel (RPE) is factored in to automatically adjust the rest of your programme: more load if all is well, a bit less if your tendon is complaining. This daily personalisation is what makes the difference compared to a fixed, paper-based programme.

Ready to start your programme?
Join the HOPP support programme designed by sports physios.
F.A.Q
Is tendinitis the same thing as quadriceps tendinopathy?
The exact medical term is “tendinopathy”, because there’s generally no clear-cut inflammation but a progressive wear of the tendon fibres linked to overload. The treatment approach stays the same: progressive strengthening and managing your sporting load.
Can I keep training with quadriceps tendinopathy?
Yes, in most cases. The idea isn’t to stop but to adapt: temporarily reduce jumping and heavy squats, while starting to strengthen the tendon as soon as possible.
How long does it take to recover from quadriceps tendinopathy?
It depends on the stage and how long you’ve had the pain. A structured programme generally takes several weeks, with a strengthening phase followed by a reconditioning phase before a full return to sport.
Is tendon rupture a common risk?
No, it’s rare and mainly affects tendinopathies that have been neglected for a long time (stage 3-4). Early treatment, from the first symptoms, greatly reduces this risk.
Do I need to stop squatting for good?
No, squatting is actually part of rehab once the load and range are adapted. The goal is to restore the tendon’s capacity to handle this exercise, not to avoid it long-term.
Does the HOPP programme replace a medical consultation?
No. HOPP is a support and rehab tool designed by sports physiotherapists, but it doesn’t replace a doctor’s opinion. If in doubt, or if the pain persists, see a health professional.
Is the programme suited to all sporting levels?
Yes. Every programme is personalised to your sport, your level and how you feel each day, whether you’re a recreational athlete or preparing for competition.